
ClarIDHy was a large, global, randomized phase 3 trial and the first to demonstrate clinical benefit with targeted therapy in advanced mIDH1 CCA1,2
The primary endpoint was progression-free survival (PFS), and secondary endpoints included overall survival, objective response rate, safety, and quality of life.2,3
TIBSOVO was studied in a phase 3, randomized, double-blind, placebo-controlled, multicenter trial in a CCA patient population reflective of that seen in clinical practice.2,3
ClarIDHy study design
TIBSOVO® was studied in a patient population reflective of that seen in a clinical practice3
Selected baseline demographics and disease characteristics (N=185)1
| TIBSOVO (n=124) |
Placebo (n=61) |
||
| Demographics | |||
|---|---|---|---|
| Median age, years (min, max) | 61 (33, 80) | 63 (40, 83) | |
| Sex | |||
| Male | 36% | 40% | |
| Female | 65% | 61% | |
| Race | |||
| White | 57% | 57% | |
| Asian | 12% | 13% | |
| Black | 0.8% | 1.6% | |
| Native Hawaiian/Other Pacific Islander | 0.8% | 0% | |
| American Indian or Alaska Native | 0.8% | 0% | |
| Disease characteristics | |||
| Prior lines of therapy | |||
| 1 prior line of therapy | 53% | 54% | |
| 2 prior lines of therapy | 47% | 46% | |
| ECOG PS | |||
| 0 | 40% | 31% | |
| 1 | 60% | 67% | |
| IDH1 mutation | |||
| R132C | 68% | 74% | |
| R132L | 17% | 12% | |
| R132G | 14% | 10% | |
| R132H | 0% | 3.3% | |
| R132S | 1.6% | 1.6% | |
| Cholangiocarcinoma type at initial diagnosis | |||
| Intrahepatic | 90% | 95% | |
| Metastatic disease | 93% | 92% | |
ECOG PS, Eastern Cooperative Oncology Group Performance Status.
Baseline characteristics
TIBSOVO® (ivosidenib tablets) was studied in a phase 3, randomized, double-blind, placebo-controlled, multicenter trial—one of the largest clinical trials to date of a targeted therapy in cholangiocarcinoma1-3


CCA, cholangiocarcinoma; ECOG PS, Eastern Cooperative Oncology Group Performance Status; IDH1, isocitrate dehydrogenase-1; mIDH1, mutated IDH1; NGS, next-generation sequencing; QD, once a day; RECIST, Response Evaluation Criteria in Solid Tumors.
Recommendation from the NCCN Clinical Practice Guidelines in Oncology
(NCCN Guidelines®)
Ivosidenib (TIBSOVO) is recommended as an NCCN category 1 subsequent-line systemic treatment option for patients with unresectable or metastatic progressive CCA with IDH1 mutations.4,a
aTo view the most recent and complete version of the guidelines, visit NCCN.org.
mIDH1, mutated isocitrate dehydrogenase-1; NCCN, National Comprehensive Cancer Network® (NCCN®).
TIBSOVO delivered significant improvements in PFS1
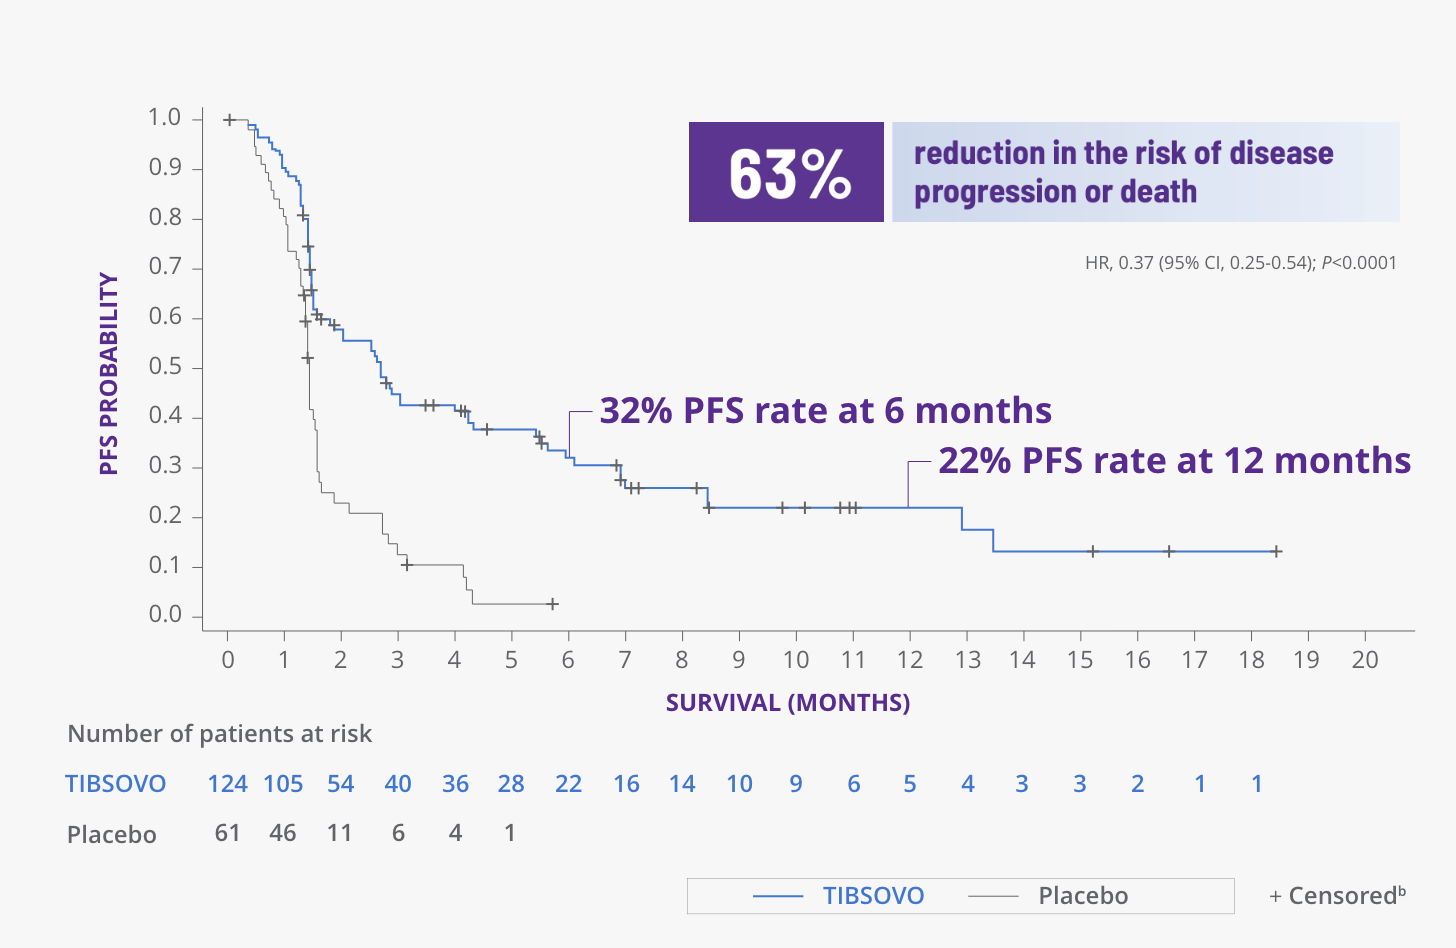
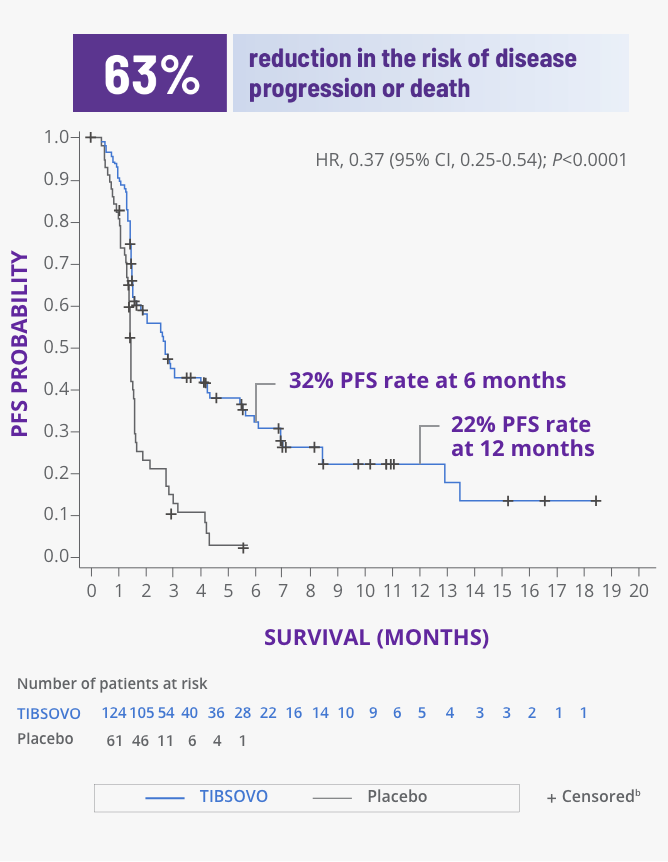
PFS for TIBSOVO vs placebo1,3
Description
Kaplan-Meier curve presenting progression-free survival (PFS) comparing TIBSOVO versus placebo in patients with previously treated IDH1-mutated cholangiocarcinoma. The x-axis spans from baseline through approximately 20 months.
The survival curves separate over time in favor of TIBSOVO. The hazard ratio was 0.37 (95% CI, 0.25–0.54; P<0.0001), corresponding to a 63% reduction in the risk of disease progression or death with TIBSOVO versus placebo. The PFS rate at 6 months was 32% with TIBSOVO, and the PFS rate at 12 months was 22% with TIBSOVO.
CI, confidence interval; HR, hazard ratio.
bPatients were censored if they were missing a baseline assessment, missing documented progression or death before data cutoff, started alternate anticancer systemic treatment, or had documented progression or death following 95 days or more from the previous adequate assessment.2
- None of the patients assigned to placebo had PFS of 6 months or greater3
- The median PFS was nearly twice as long for patients assigned to TIBSOVO compared with placebo (2.7 months [95% CI, 1.6-4.2] versus 1.4 months [95% CI, 1.4-1.6])3
Treatment duration within ClarIDHy trial
MEDIAN TREATMENT DURATION
2.8 months
with TIBSOVO1
(range, 0.1 to 34.4 months)
1.6 months
with placebo2
(range, 0 to 6.9 months)
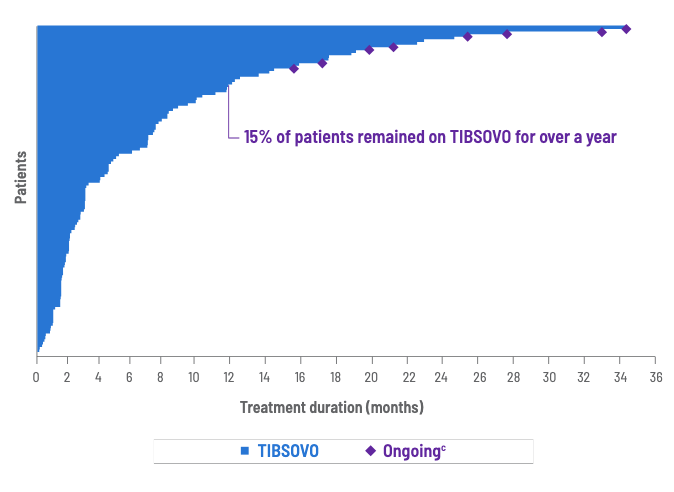
Treatment duration for all patients treated with TIBSOVO2

Description
Swimmer plot presenting treatment duration for all patients treated with TIBSOVO in previously treated IDH1-mutated cholangiocarcinoma. The x-axis spans from 0 to 36 months of treatment duration. Each patient is represented individually, with ongoing patients indicated by a separate marker. 15% of patients remained on TIBSOVO for over a year.
cOngoing as of data cutoff (May 31, 2020).
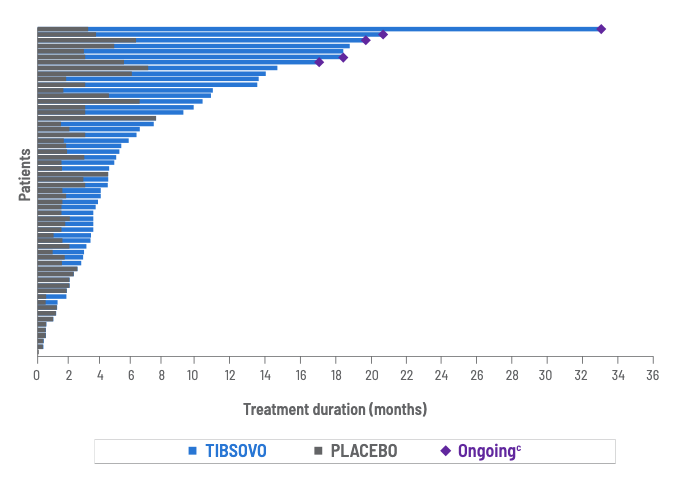
Treatment duration for all patients treated with placebo, including those who crossed over to TIBSOVO2

Description
Swimmer plot presenting treatment duration for all patients treated with placebo, including those who crossed over to TIBSOVO, in previously treated IDH1-mutated cholangiocarcinoma. The x-axis spans from 0 to 36 months of treatment duration. Each patient is represented individually, with placebo duration shown in gray and TIBSOVO duration following crossover shown in blue. Ongoing patients are indicated by a separate marker.
cOngoing as of data cutoff (May 31, 2020).
Overall survival (OS) data with TIBSOVO
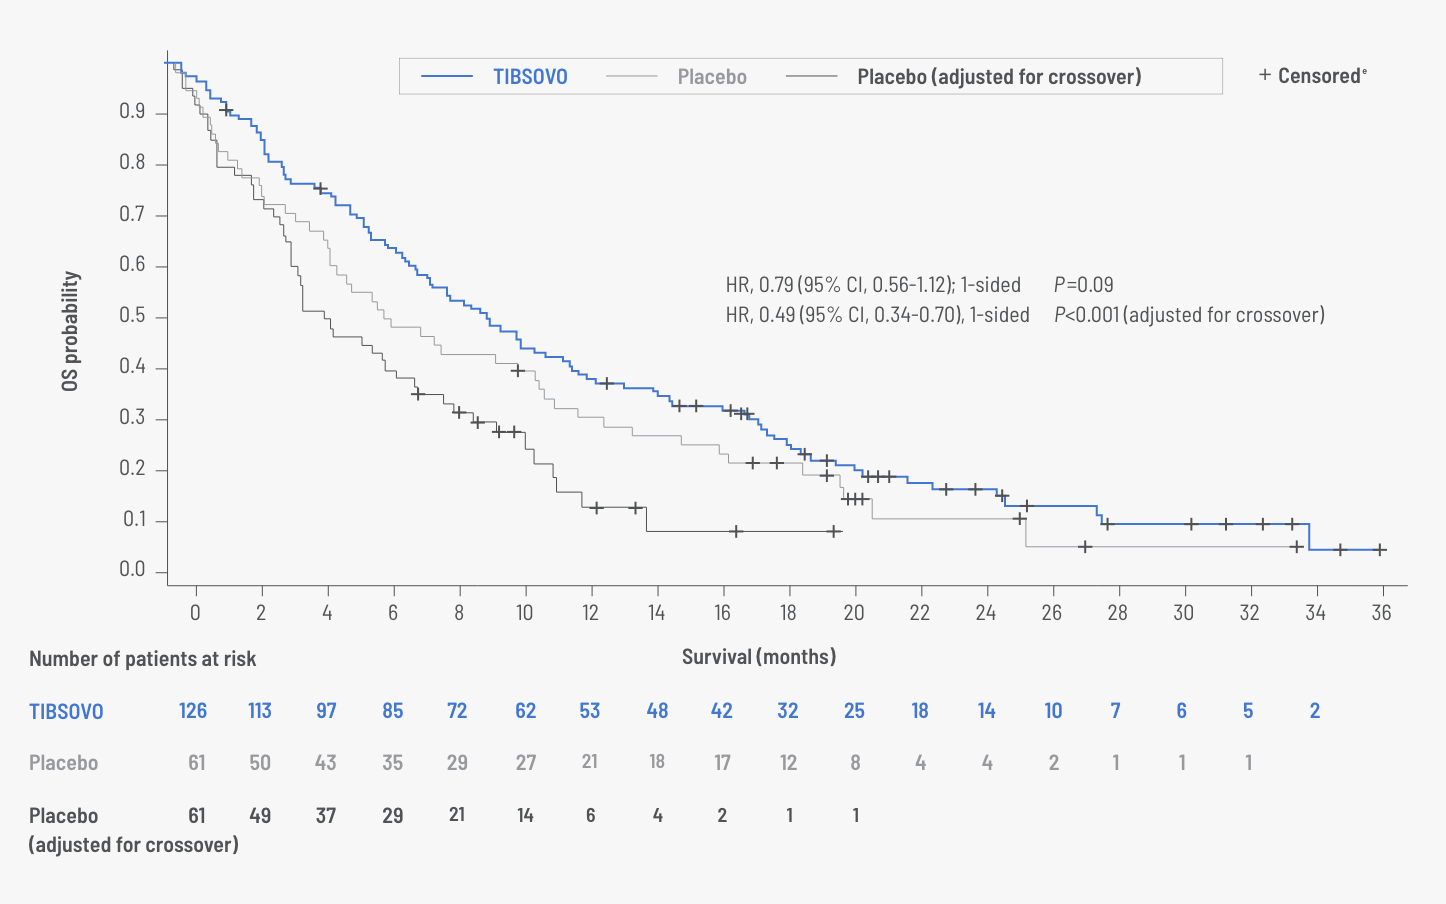
OS for TIBSOVO vs placebo (intent-to-treat set)2,d
|
TIBSOVO n=126 |
Placebo n=61 |
Placebo (adjusted for crossover) n=61 |
|
|---|---|---|---|
| Number of events (%) | 100 (79.4) | 50 (82.0) | 49 (80.3) |
| Median OS, months | 10.3 | 7.5 | 5.1 |
| 12-month rate | 43% (95% CI, 34%-51%) |
36% (95% CI, 24%-48%) |
36% (95% CI, 24%-48%) |
CI, confidence interval; HR, hazard ratio.
Description
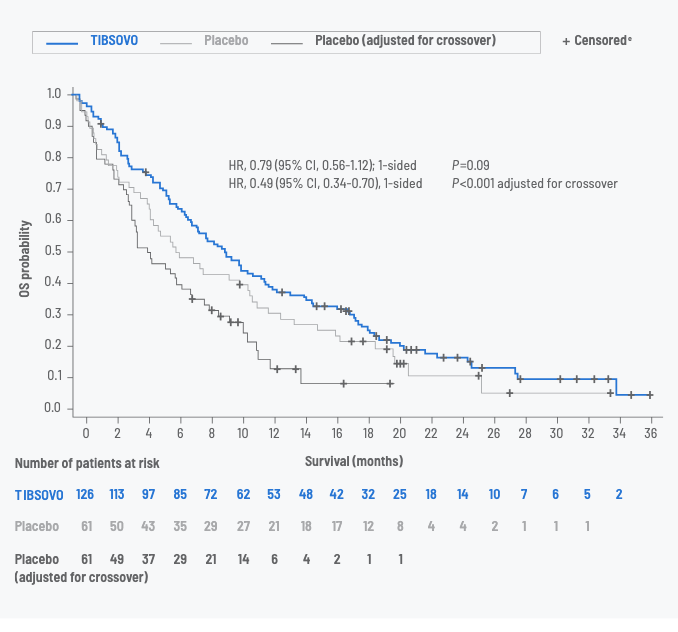
Kaplan-Meier curve presenting overall survival (OS) in patients with previously treated IDH1-mutated cholangiocarcinoma, comparing TIBSOVO, placebo, and placebo adjusted for crossover. The x-axis spans from baseline through approximately 36 months. Numbers of patients at risk are displayed below the x-axis for each arm at each timepoint.
For the unadjusted comparison, the hazard ratio was 0.79 (95% CI, 0.56–1.12; 1-sided P=0.09). For the crossover-adjusted comparison, the hazard ratio was 0.49 (95% CI, 0.34–0.70; 1-sided P<0.001). The three curves separate over time, with the TIBSOVO arm remaining higher than both the placebo and crossover-adjusted placebo arms throughout follow-up.
dOS results are based on the final analysis of OS (based on 150 deaths), which occurred 16 months after the final analysis of PFS.1
ePatients without documentation of death at the time of the data cutoff for analysis were censored at the date the subject was last known to be alive or the data cutoff date, whichever was earlier.2
- Among the 61 patients in the placebo arm, 70% crossed over to receive TIBSOVO1
- These patients continued to be grouped within their original randomized assignment for analysis purposes2
- As a result, OS data may be confounded by the crossover2
- A statistical model known as rank-preserving structural failure time (RPSFT) was used to recreate the placebo curve as if crossover had not occurredf,g
- When adjusted for crossover, median OS for the placebo group was 5.1 months (95% CI, 3.8-7.6 months; HR, 0.49 [95% CI, 0.34-0.70])
fThis prespecified model, known as RPSFT, is one of the most commonly used statistical methods to adjust for treatment switching in oncology trials. This sensitivity analysis was exploratory, and appropriate multiplicity adjustments were not applied.
gThe RPSFT model is based on the assumption that the treatment effect of TIBSOVO is the same for all individuals, regardless of when treatment is received. This assumption was not verified.
More than half (51%) of patients receiving TIBSOVO achieved stable disease3
Disease control rate3,h
53%
with TIBSOVO
28%
with placebo
ORR, objective response rate; SD, stable disease.
hThe disease control rate (ORR + SD) was due mostly to the SD rate (an ORR of 2% [3 partial responses] and an SD rate of 51% with TIBSOVO vs an ORR of 0% and an SD rate of 28% with placebo).
Health-related quality of life (QoL)
- CCA is associated with an impaired QoL, a metric that is increasingly regarded as a crucial endpoint in clinical trials5
- Health-related QoL was assessed using two tools; the EORTC QLQ-C30, a generic cancer questionnaire, and the EORTC QLQ-BIL21, a disease-specific module2
- TIBSOVO was favored on physical functioning, as well as subscales such as pain, emotional functioning, cognitive functioning, dyspnea, anxiety, and tiredness2
- Analyses of the QoL data were limited by small sample sizes.2 Assessments depicted were at Cycle 2 Day 12,i
EORTC QLQ-C30 global health status/QoL and functional subscales6


Description
Forest plot presenting EORTC QLQ-C30 global health status/quality of life (QoL) and functional subscale scores, reported as least squares (LS) mean difference (95% CI) comparing TIBSOVO versus placebo in patients with previously treated IDH1-mutated cholangiocarcinoma. Values to the right of zero favor TIBSOVO; values to the left favor placebo.
The following subscales are presented, each with point estimates and 95% confidence intervals displayed: global health status/QoL, physical functioning, social functioning, role functioning, cognitive functioning, and emotional functioning. The point estimates for all six subscales fall to the right of zero, indicating numeric differences in favor of TIBSOVO across all subscales assessed.
EORTC QLQ-C30 symptoms subscales6


Description
Forest plot presenting EORTC QLQ-C30 symptoms subscale scores, reported as least squares (LS) mean difference (95% CI) comparing TIBSOVO versus placebo in patients with previously treated IDH1-mutated cholangiocarcinoma. For symptom subscales, values to the left of zero favor TIBSOVO (indicating fewer symptoms); values to the right favor placebo.
The following symptom subscales are presented, each with point estimates and 95% confidence intervals displayed: fatigue, nausea and vomiting, pain, dyspnea, insomnia, appetite loss, constipation, diarrhea, and financial difficulties. The point estimates for fatigue, nausea and vomiting, pain, dyspnea, insomnia, diarrhea, and financial difficulties fall to the left of zero, indicating numeric differences in favor of TIBSOVO. The point estimates for appetite loss and constipation fall to the right of zero, indicating numeric differences in favor of placebo.
EORTC QLQ-BIL21 subscales6


Description
Forest plot presenting EORTC QLQ-BIL21 subscale scores, reported as least squares (LS) mean difference (95% CI) comparing TIBSOVO versus placebo in patients with previously treated IDH1-mutated cholangiocarcinoma. For symptom subscales, values to the left of zero favor TIBSOVO (indicating fewer symptoms); values to the right favor placebo.
The following subscales are presented, each with point estimates and 95% confidence intervals displayed: weight loss, drains, treatment side effects, anxiety, pain, tiredness, jaundice, and eating. The point estimates for weight loss, treatment side effects, anxiety, pain, and tiredness fall to the left of zero, indicating numeric differences in favor of TIBSOVO. The point estimates for drains, jaundice, and eating fall to the right of zero, indicating numeric differences in favor of placebo.
These QoL analyses were exploratory, and appropriate multiplicity adjustments were not applied. Results of these individual components need cautious interpretation and could represent chance findings.
CI, confidence interval; EORTC QLQ-BIL21, EORTC QLQ cholangiocarcinoma and gallbladder cancer module; EORTC QLC-C30, European Organisation for Research and Treatment of Cancer Quality of Life Questionnaire Core 30; LS, least squares.
iAt baseline: n=53 for placebo and n=114 for TIBSOVO (QLQ-C30); n=52 for placebo and n=108 for TIBSOVO (QLQ-BIL21). At Cycle 2 Day 1: n=24 for placebo and n=68 for TIBSOVO (QLQ-C30); n=23 for placebo and n=68 for TIBSOVO (QLQ-BIL21). At Cycle 3 Day 1: n=12 for placebo and n=52 for TIBSOVO (QLQ-C30); n=12 for placebo and n=52 for TIBSOVO (QLQ-BIL21).2
Consider TIBSOVO as a second-line targeted treatment
for mIDH1 CCA.1
Indication & Important Safety Information
INDICATION
TIBSOVO is indicated for patients with a susceptible isocitrate dehydrogenase-1 (IDH1) mutation as detected by an FDA-approved test for the treatment of adult patients with locally advanced or metastatic cholangiocarcinoma who have been previously treated.
IMPORTANT SAFETY INFORMATION
WARNINGS AND PRECAUTIONS
QTc Interval Prolongation: Patients treated with TIBSOVO can develop QT (QTc) prolongation and ventricular arrhythmias. Concomitant use of TIBSOVO with drugs known to prolong the QTc interval (eg, anti-arrhythmic medicines, fluoroquinolones, triazole anti-fungals, 5-HT3 receptor antagonists) and CYP3A4 inhibitors may increase the risk of QTc interval prolongation. Conduct monitoring of electrocardiograms (ECGs) and electrolytes. In patients with congenital long QTc syndrome, congestive heart failure, or electrolyte abnormalities, or in those who are taking medications known to prolong the QTc interval, more frequent monitoring may be necessary. Interrupt TIBSOVO if QTc increases to greater than 480 msec and less than 500 msec. Interrupt and reduce TIBSOVO if QTc increases to greater than 500 msec. Permanently discontinue TIBSOVO in patients who develop QTc interval prolongation with signs or symptoms of life-threatening arrhythmia.
