
TIBSOVO (ivosidenib tablets) is the only targeted therapy that was studied in a phase 3 trial specifically designed for newly diagnosed patients with mIDH1 AML1
TIBSOVO + azacitidine was studied in a global, phase 3, multicenter, randomized, double-blind, placebo-controlled trial in an IC-ineligible patient population reflective of that seen in clinical practice.1,2
AGILE study design
AGILE study design1,3
- Efficacy was established on the basis of event-free survival (EFS), overall survival (OS), and rate and duration of complete remission (CR)1,a,b
- Treatment failure was defined as failure to achieve CR by Week 24. Patients who achieved CRh but not CR did not meet the EFS definition of treatment success1,c
AML, acute myeloid leukemia; CRh, complete remission with partial hematologic recovery; ECOG PS, Eastern Cooperative Oncology Group Performance Status; EORTC QLC-C30, European Organisation for Research and Treatment of Cancer Core Quality of Life Questionnaire; EQ-5D-FL, 5-level EuroQol Five Dimensions Questionnaire (descriptive system and visual analogue scale); HMA, hypomethylating agent; IV, intravenous; LVEF, left ventricular ejection fraction; mIDH1, mutated isocitrate dehydrogenase-1; MDS, myelodysplastic syndromes; MPN, myeloproliferative neoplasms; ORR, objective response rate; QD, once a day; SC, subcutaneous.
See baseline characteristics
Baseline patient demographics and disease characteristics1
| TIBSOVO® (500 mg daily) + azacitidine (n=72) |
Placebo + azacitidine (n=74) |
||
| Median age, years (min, max) | 76 (58, 84) | 76 (45, 94) | |
| Age categories, n (%) | |||
| <65 years | 4 (6) | 4 (5) | |
| ≥65 years to <75 years | 29 (40) | 27 (36) | |
| ≥75 years | 39 (54) | 43 (58) | |
| Cytogenetic risk status,a n (%) | |||
| Favorable | 3 (4) | 7 (9) | |
| Intermediate | 48 (67) | 44 (59) | |
| Poor | 16 (22) | 20 (27) | |
| Other | 3 (4) | 1 (1) | |
| Missing | 2 (3) | 2 (3) | |
| ECOG PS, n (%) | |||
| 0 | 14 (19) | 10 (14) | |
| 1 | 32 (44) | 40 (54) | |
| 2 | 26 (36) | 24 (32) | |
| Transfusion dependent at baseline,b n (%) | 39 (54) | 40 (54) | |
| Type of AML, n (%) | |||
| De novo AML | 54 (75) | 53 (72) | |
| Secondary AML | 18 (25) | 21 (28) | |
| Therapy-related AML | 2 (3) | 1 (1) | |
| MDS related | 10 (14) | 12 (16) | |
| MPN related | 4 (6) | 8 (11) | |
aCytogenic risk status: Investigators used the NCCN Clinical Practice Guidelines in Oncology (NCCN Guidelines®).1
bPatients were defined as transfusion dependent at baseline if they received any RBC or platelet transfusion within 56 days prior to the first dose of study treatment.1
AML, acute myeloid leukemia; ECOG PS, Eastern Cooperative Oncology Group Performance Status; MDS, myelodysplastic syndromes; MPN, myeloproliferative neoplasms; NCCN, National Comprehensive Cancer Network®; RBC, red blood cell.
AML, acute myeloid leukemia; IC, induction chemotherapy; mIDH1, mutant isocitrate dehydrogenase‑1.
TIBSOVO + azacitidine is proven to significantly increase overall survival (OS)1
More than threefold improvement in mOS with TIBSOVO + AZA vs placebo + AZA1,4


Description
Kaplan-Meier curve presenting overall survival data from two analyses — a primary OS analysis and a long-term follow-up OS analysis — comparing TIBSOVO plus azacitidine (AZA) versus placebo plus AZA in patients with IDH1-mutated acute myeloid leukemia (AML).
In the primary OS analysis, the survival curves separate over time in favor of TIBSOVO + AZA. Median overall survival was 24.0 months with TIBSOVO + AZA (95% CI, 11.3–34.1) compared with 7.9 months with placebo + AZA (95% CI, 4.1–11.3). The hazard ratio was 0.44 (P=0.0010).
In the long-term follow-up OS analysis, median overall survival was 29.3 months with TIBSOVO + AZA (95% CI, 13.2–NR) compared with 7.9 months with placebo + AZA (95% CI, 4.1–11.3). The hazard ratio was 0.42 (P<0.0001). The survival curves maintain separation through approximately 50 months of follow-up.
Primary OS analysis
24.0 months mOS with TIBSOVO + azacitidine (95% CI, 11.3–34.1) vs 7.9 months with azacitidine alone (95% CI, 4.1–11.3)1,a
- 56% reduction in risk of death (HR, 0.44 [95% CI, 0.27–0.73]; P=0.0010)1
- The percentage of OS events at the time of analysis was 39% (n=28) and 62% (n=46) in the TIBSOVO + azacitidine and placebo + azacitidine arms, respectively1
Long-term follow-up OS analysis
29.3 months mOS with TIBSOVO + azacitidine (95% CI, 13.2–NR) vs 7.9 months with azacitidine alone (95% CI, 4.1–11.3)6,b
- 58% reduction in risk of death (HR, 0.42 [95% CI, 0.27–0.65]; P<0.0001)6
aIn the primary analysis from the AGILE study, 146 patients were 1:1 randomized: 72 to TIBSOVO + AZA and 74 to PBO + AZA.1,3 The data cutoff date of the primary analysis from the AGILE study was March 2021 with a median follow-up of 15.1 months for the OS analysis.
bIn the long-term follow-up analysis from the AGILE study, 148 patients were 1:1 randomized: 73 to TIBSOVO + AZA and 75 to PBO + AZA.2,4 The data cutoff date of the long-term follow-up analysis from the AGILE study was June 2022 with a median follow-up of 28.6 months for the OS analysis.
Overall survival benefit with TIBSOVO + azacitidine increased over time compared to placebo + AZA
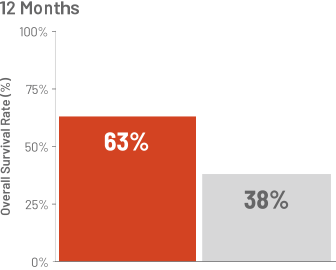
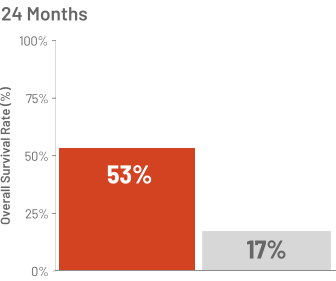
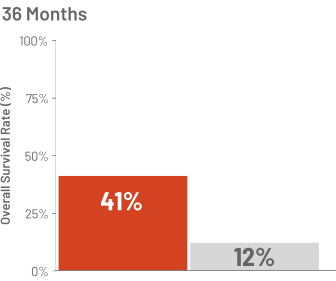
Greater than 3X increase in OS rates at 24 and 36 months with TIBSOVO + azacitidine3

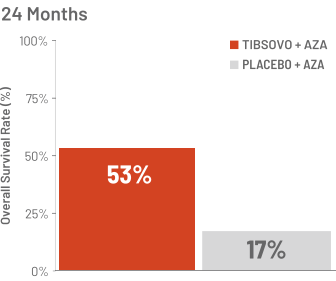
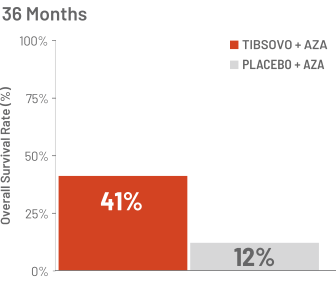
Description
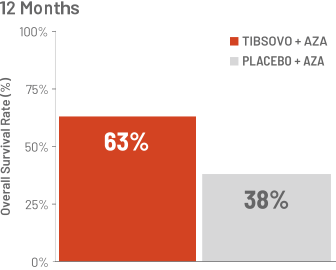
Bar chart presenting overall survival rates at 12, 24, and 36 months in patients treated with TIBSOVO plus azacitidine (AZA) versus placebo plus AZA.
At 12 months, the overall survival rate was 63% with TIBSOVO + AZA compared with 38% with placebo + AZA.
At 24 months, the overall survival rate was 53% with TIBSOVO + AZA compared with 17% with placebo + AZA.
At 36 months, the overall survival rate was 41% with TIBSOVO + AZA compared with 12% with placebo + AZA.
AML, acute myeloid leukemia; AZ, azacitidine; CI, confidence interval; ECOG PS, Eastern Cooperative Oncology Group Performance Status; HR, hazard ratio; IDH1, isocitrate dehydrogenase‑1; mOS, median overall survival; PBO, placebo; WHO, World Health Organization.
TIBSOVO + azacitidine demonstrated rapid and durable remissions2
TIBSOVO + azacitidine demonstrated significantly higher rates of CR and CR+CRh compared with azacitidine (P<0.0001)1,c
Description
Graphic presenting complete remission (CR) and composite remission (CR+CRh) rates in patients treated with TIBSOVO plus azacitidine versus placebo plus azacitidine.
With TIBSOVO plus azacitidine, the CR rate was 47% (95% CI, 35–59) and the CR+CRh rate was 51% (95% CI, 39–63).
With placebo plus azacitidine, the CR rate was 15% (95% CI, 8–25) and the CR+CRh rate was 18% (95% CI, 10–28).
- Median duration of CR was not estimable (NE) as of the data cutoff date in the TIBSOVO + azacitidine arm (95% CI,13.0-NE) and was 11.2 months in the azacitidine arm (95% CI, 3.2-NE)1
- Of the patients who achieved CR with TIBSOVO + azacitidine2,3
- 88% remained in remission at 12 months (95% CI, 67.5-96.2)d
- 59% remained in remission at 24 months (95% CI, 17.7-85.1)d
- 38% of patients receiving TIBSOVO + azacitidine achieved CR by Week 24 compared with 11% of patients in the placebo + azacitidine arm2
Patients on TIBSOVO + AZA achieved higher rates of MRD negativity
30% of patients were MRD-negative by Cycle 14 in the AGILE trial4,e,f
- All patients on TIBSOVO + AZA who achieved MRD-negativity also achieved CR
Median time to response with TIBSOVO + azacitidine2
- First response (CR, CRi, CRp, PR, or MLFS): 2.1 months (range, 1.7‑7.5)
- CR: 4.3 months (range, 1.7‑9.2)
- CR+CRh: 4.0 months (range, 1.7‑8.6)
cCR was defined as <5% blasts in the bone marrow and no Auer rods, absence of extramedullary disease, full recovery of peripheral blood counts (absolute neutrophil count ≥1000/μL and platelets ≥100,000/μL), and independence of red blood cell transfusions.5 CRh was defined as <5% blasts in the bone marrow and no Auer rods, absence of extramedullary disease, and partial recovery of peripheral blood counts (absolute neutrophil count >500/μL and platelets ≥50,000/μL).1,3
dPer Kaplan-Meier estimation.3
ePatients who achieved MRD-negativity with PBO + AZA were excluded from further analysis due to small patient numbers.4
fMRD analysis was performed with a 26-gene NGS panel, including IDH1, FLT3, and NPM1.4
CR, complete remission; CRh, complete remission with partial hematologic recovery; CRi, complete remission with incomplete hematologic recovery; CRp, complete remission with incomplete platelet recovery; MLFS, morphologic leukemia-free state; PR, partial remission.
TIBSOVO + azacitidine resulted in rapid neutrophil recovery and reduction in bone marrow blasts7,g-i
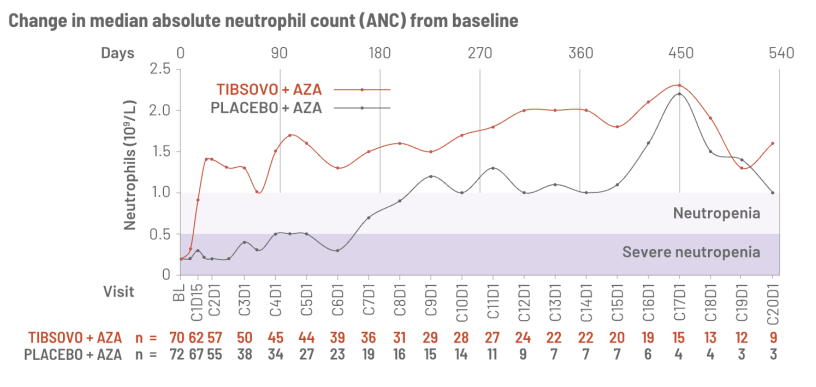
gBL denotes baseline, defined as a median ANC value of 0.2 x 10⁹/L for the TIBSOVO + AZA arm and placebo + AZA arm; CxDy indicates Cycle x Day y.7
hShading denotes neutropenia and severe neutropenia, defined as ANC values of <1.0 x 10⁹/L and <0.5 x 10⁹/L, respectively.7
iMedian values are presented to avoid the potential masking influence of outliers resulting from differentiation of leukocytosis, which may be possible with reporting the mean values.7
The graph shows the change in median absolute neutrophil count from baseline over time in patients treated with TIBSOVO plus azacitidine versus placebo plus azacitidine. Median ANC increased early with TIBSOVO plus azacitidine and generally remained above the neutropenia threshold throughout follow-up. In the placebo plus azacitidine arm, median ANC remained lower during the earlier cycles before increasing over time.
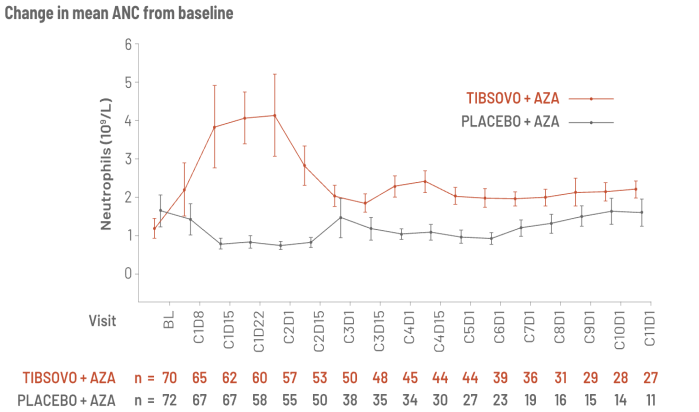
The graph shows mean absolute neutrophil count (ANC) over time in patients treated with TIBSOVO plus azacitidine versus placebo plus azacitidine. Mean ANC increased early with TIBSOVO plus azacitidine and generally remained higher throughout follow-up. In the placebo-plus-azacitidine arm, mean ANC decreased during the earlier cycles before gradually increasing over time.
BL denotes baseline, defined as the last assessment before start of study treatment; CxDy indicates Cycle x Day y; error bars indicate mean +/- standard error.
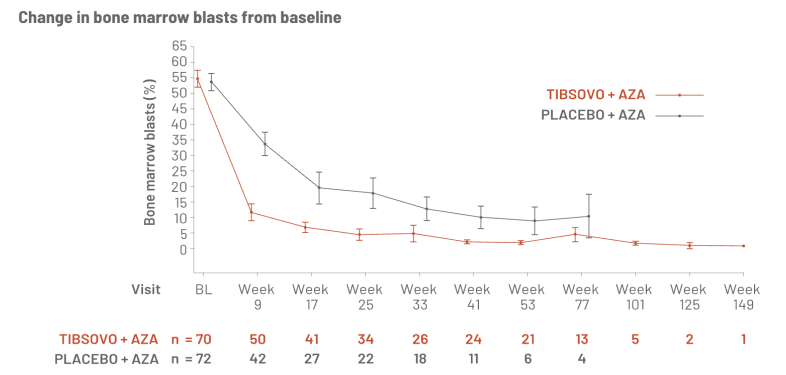
- Participants in the trial were to follow a study center visit schedule that included a bone marrow aspirate/biopsy and peripheral blood sampling to evaluate IDH1-mutated cells and to assess disease status and response3
BL denotes baseline, defined as the last assessment before start of study treatment; error bars indicate mean +/- standard error.
The graph shows changes in bone marrow blast percentage from baseline over time in patients treated with TIBSOVO plus azacitidine versus placebo plus azacitidine. Bone marrow blast levels decreased rapidly with TIBSOVO plus azacitidine and generally remained low throughout follow-up. In the placebo-plus-azacitidine arm, bone marrow blast levels decreased more gradually and generally remained higher across the available follow-up visits.
Significant improvements in event-free survival (EFS)1,j
Treatment with TIBSOVO + azacitidine resulted in significant improvements in EFS compared with azacitidine
| Endpoint | TIBSOVO + azacitidine (n=72) |
Placebo + azacitidine (n=74) |
|
|---|---|---|---|
| EFS, events (%) | 47 (65) | 62 (84) | |
| Treatment failure | 43 (60) | 59 (80) | |
| Relapse | 3 (4) | 2 (3) | |
| Death | 1 (1) | 1 (1) | |
| Hazard ratiok (95% CI) | 0.35 (0.17-0.72) | ||
| p valuel | 0.0038 | ||
jEFS was defined as time from randomization until treatment failure (ie, failure to achieve CR by Week 24), relapse from remission, or death from any cause, whichever occurred first.1
kHazard ratio was estimated using a Cox proportional hazards model stratified by the randomization stratification factors (AML status and geographic region) with placebo + azacitidine as the denominator.
lTwo-sided P value boundary for EFS is 0.0095 and was calculated from the log-rank test stratified by the randomization stratification factors (AML status and geographic region).
TIBSOVO + azacitidine demonstrated higher EFS rates compared to azacitidine alone5
Description
Bar charts presenting event-free survival (EFS) rates at 12 months and 18 months in patients treated with TIBSOVO plus azacitidine versus placebo plus azacitidine.
At 12 months, the EFS rate was 37.4% (95% CI, 25.9–48.9) with TIBSOVO plus azacitidine compared with 12.2% (95% CI, 4.3–24.4) with placebo plus azacitidine.
At 18 months, the EFS rate was 33.3% (95% CI, 20.9–46.2) with TIBSOVO plus azacitidine compared with 6.1% (95% CI, 0.7–20.9) with placebo plus azacitidine.
AML, acute myeloid leukemia; CI, confidence interval; CR, complete remission.
More than half of patients achieved transfusion independence with TIBSOVO + azacitidine
Transfusion independence among patients who were transfusion dependent at baseline3,m,n
Description
Horizontal bar chart presenting transfusion independence among patients who were transfusion dependent at baseline, comparing TIBSOVO plus azacitidine versus placebo plus azacitidine.
The transfusion independence rate was 54% with TIBSOVO plus azacitidine compared with 17% with placebo plus azacitidine (P=0.0004).
Postbaseline RBC and platelet transfusion independence regardless of baseline transfusion status2,n
Description
Horizontal bar chart presenting postbaseline red blood cell (RBC) and platelet transfusion independence regardless of baseline transfusion status, comparing TIBSOVO plus azacitidine versus azacitidine alone.
The transfusion independence rate was 63% with TIBSOVO plus azacitidine compared with 51% with azacitidine alone (2-sided P=0.21).
mPostbaseline transfusion independence is defined as a period of ≥56 days with no transfusion after the start of study treatment and on or before the end of study treatment + 28 days, disease progression, confirmed relapse, death, or data cutoff date, whichever was earlier.6
nThe 95% confidence interval in the transfusion independence analysis was 37.2–69.9 for the TIBSOVO + azacitidine arm and 7.2–32.1 for the placebo + azacitidine arm.4
RBC, red blood cell.
NCCN Guidelines® recommends ivosidenib (TIBSOVO) + azacitidine as a category 1 preferred treatment option for newly diagnosed patients
≥18 years of age with mIDH1 AML who are not candidates for intensive remission induction therapy8
INDICATIONS
TIBSOVO is indicated for patients with a susceptible isocitrate dehydrogenase-1 (IDH1) mutation as detected by an FDA-approved test with:
Newly Diagnosed Acute Myeloid Leukemia (AML)
- In combination with azacitidine or as monotherapy for the treatment of newly diagnosed AML in adults 75 years or older, or who have comorbidities that preclude the use of intensive induction chemotherapy